
Educational content by JabKasai Longevity. Editorial policy
Content updated:
Medical schema
How to read this guide safely
This visual map connects Prostatitis to anatomy, symptom triage, professional care and the limits of bodywork claims.
- 01
Observe the pattern
Location, timing, intensity, triggers and associated urinary, sexual, pain or systemic changes.
- 02
Check red flags
Fever, chills, burning urination, retention, vomiting or feeling seriously unwell moves first.
- 03
Choose the care path
Urine testing, culture, antibiotics, imaging or urgent care may be needed depending on severity.
- 04
Keep clear boundaries
No massage, pressure or traditional interpretation should bypass red-flag triage.
Prostatitis is not one simple disease. It can mean acute bacterial infection, recurrent bacterial infection, inflammation or chronic pelvic pain syndrome.
What this page is for
That distinction matters because infection with fever requires a different response than long-term pain with pelvic floor overlap and negative tests. The goal is to help an adult reader move from a private, vague concern into a structured description that can be discussed with a qualified professional. The tone is calm, medical and non-erotic: symptoms are not shameful, and they should not be turned into spectacle.
How to read the symptom
For Prostatitis, context matters because male intimate health works as a shared system. Blood flow, nerves, hormones, prostate, bladder, testicles, pelvic floor, bowel habits, sleep, mood and relationship pressure can overlap. Reading those layers together is more precise than choosing one explanation too early.
Common patterns to note
Useful observation is concrete. Before looking for a remedy or comparing practitioners, note whether one of these patterns fits:
- Perineal or pelvic pain.
- Burning, urgency or frequent urination.
- Pain with ejaculation.
- Fever and illness in acute forms.
- Recurring flares over time.
Possible causes without self-diagnosis
This topic can sit near several possible causes, including bacterial infection, inflammation, pelvic floor overactivity, chronic pain, stress, bladder irritation, previous infection. This list is not a self-treatment menu. It is a reminder that the same complaint can mean different things depending on age, history, medicines, exposures, pain type and examination results.
Red flags and urgency
Fever, chills, significant pain, difficulty urinating, blood, feeling unwell or rapid worsening requires prompt medical assessment.
Urgency is not about bravery or embarrassment. It is about time-sensitive risk. Sudden severe testicular pain, inability to urinate, fever with urinary or pelvic symptoms, new swelling, trauma, blood, discharge, severe pain, chest symptoms during sex or neurological signs can change the decision immediately. In those situations, waiting to see whether massage, supplements, heat, stretching or breathing helps can be unsafe.
If you are unsure whether a symptom is urgent, it is safer to contact a medical service than to test the body. This site cannot triage an individual in real time.
Questions to bring to care
Many men find it hard to explain intimate symptoms during a short appointment. Written questions make the conversation simpler and more complete. For this topic, useful questions include:
- Was infection tested?
- Are symptoms acute or chronic?
- Is ejaculation painful?
- Which treatments helped or worsened the pattern?
Where Jab Kasai and bodywork fit
Prostate or pelvic massage is not appropriate as a first response when infection, fever, severe pain or uncertain diagnosis is possible. On JABKASAI, traditional bodywork is described as cultural or wellbeing context, not as a substitute for diagnosis. A practitioner who promises to cure infection, infertility, erectile dysfunction, prostate disease, urinary obstruction, hormone deficiency or testicular disease is making a claim outside a responsible scope.
What not to assume
Do not treat prostatitis as one problem with one solution. The term covers different categories. It is also risky to assume that a story read online, a forum answer or a practitioner promise applies to every body. Male intimate health varies by age, circulation, medicines, stress, past infections, surgery, fertility goals and relationship context.
Practical next step
Ask for evaluation that separates infection, inflammation, chronic pain and muscle tension before long-term strategies. If the symptom is mild and non-urgent, a short one- to two-week log can help. Record sleep, stress, alcohol, exercise, sitting time, digestion, sexual activity, pain level, urinary changes and medicines. If the symptom persists, progresses, recurs or creates distress, move from logging to care.
Reader checklist
- Write the first date, main location, intensity and whether the symptom is improving, stable or worsening.
- Put urinary, sexual, bowel, testicular, pelvic, sleep, medicine and stress changes on the same page.
- Check urgent signs before considering massage, supplements, stretching or sexual testing.
- Ask whether an objective exam or test would answer the question better than guessing.
- Keep professional boundaries visible: consent, hygiene, scope, stop signal and referral rules.
Bottom line
Prostatitis should be handled with precision rather than panic or shame. The safest sequence is simple: name the symptom, describe the pattern, check red flags, seek care when needed and keep wellbeing practices in their proper place. That sequence protects health, dignity and decision-making.
Sources reviewed
- NIDDK: Prostatitis
- Mayo Clinic: Prostatitis symptoms and causes
- MedlinePlus: Sexual problems in men
- MedlinePlus: Male reproductive system
- NIDDK: Prostate problems
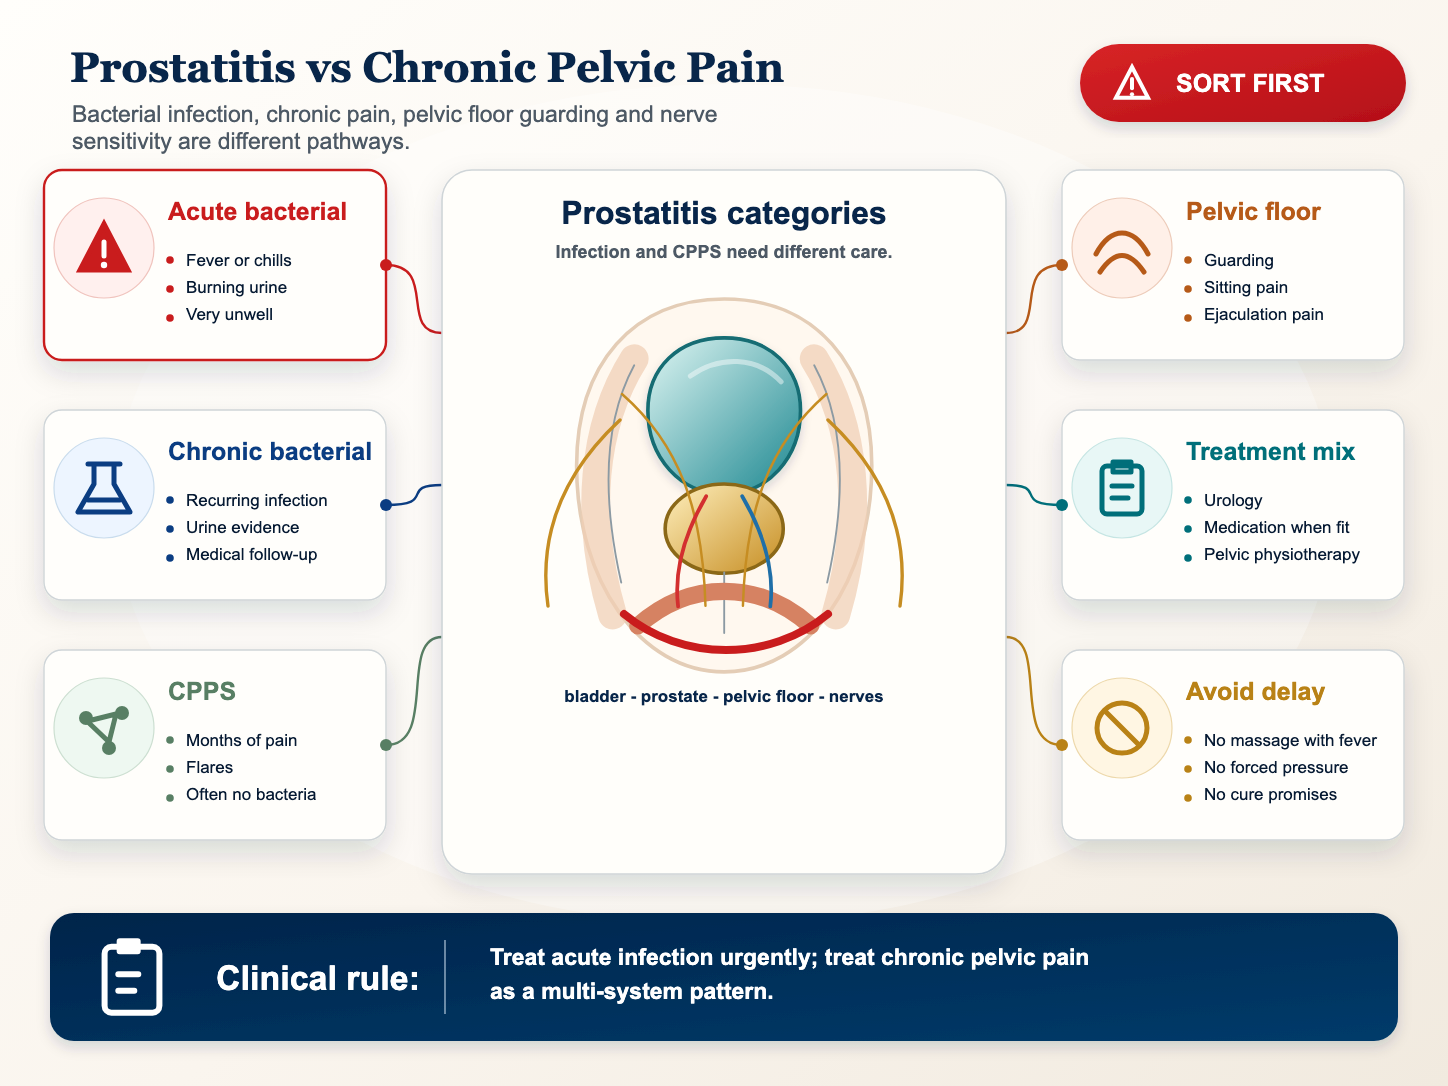
Prostatitis is not one simple disease. It can mean acute bacterial infection, chronic bacterial infection, inflammatory findings without symptoms, or chronic prostatitis/chronic pelvic pain syndrome. Those categories matter because fever and infection call for a different response than long-term pain, pelvic floor guarding, nerve sensitivity or stress-linked flares.
Why this guide matters
Prostatitis Symptoms, Causes and Treatment belongs inside a larger male health map. A symptom or question rarely comes from one isolated structure. Blood flow, nerves, hormones, muscles, sleep, stress, medication, urinary habits, bowel habits and relationship context can all change how the body feels. The purpose of this page is to give a careful orientation before a reader compares treatments, bodywork traditions or online claims.
Prostatitis is not one simple disease. It can mean acute bacterial infection, chronic bacterial infection, inflammatory findings without symptoms, or chronic prostatitis/chronic pelvic pain syndrome. Those categories matter because fever and infection call for a different response than long-term pain, pelvic floor guarding, nerve sensitivity or stress-linked flares. The practical goal is not to diagnose from a screen. It is to improve the quality of the next decision: what to observe, what to record, what is safe to try as general wellbeing support, and what should move directly to a qualified clinician.
Simple anatomy and function
The prostate can become inflamed or infected, but chronic pelvic pain may involve muscles, nerves, bladder behavior, bowel habits, pain sensitization, stress and previous infection. Treatment may include antibiotics when infection is likely or proven, alpha blockers in selected urinary patterns, anti-inflammatory or pain strategies, pelvic floor physiotherapy, lifestyle work and multidisciplinary care. This is why JABKASAI uses a conservative frame. Traditional language can be meaningful, but it should not replace anatomy, physiology or clinical triage. When a claim is medical, the evidence and assessment pathway must also be medical.
Common patterns to notice
Useful observation is specific. The reader should notice location, timing, intensity, triggers, duration and associated changes instead of using one vague label. For this topic, the most useful patterns include:
- Pain or pressure in the perineum, pelvis, penis, testicles, rectum or lower abdomen.
- Burning urination, urgency, frequency, weak stream or night urination.
- Pain during or after ejaculation, sometimes lasting minutes or hours.
- Fever, chills, acute illness or rapidly worsening urinary symptoms.
- Long-term flares triggered by sitting, stress, constipation, cycling, sex or exercise.
Medical triage before interpretation
The first triage question is whether infection or urgent urinary obstruction is possible; only then should chronic pelvic pain and pelvic floor patterns be explored. A serious educational page must keep this order clear. First ask whether the situation is urgent, new, severe, persistent or associated with systemic symptoms. Only after that should the reader think about lifestyle, stress, bodywork, sexual confidence or traditional wellbeing language.
Fever, chills, severe burning urination, inability to urinate, blood in urine, severe back pain, vomiting or feeling very unwell needs prompt medical assessment.
Questions worth bringing to care
- Was urine testing performed, and were bacteria found?
- Is this an acute illness or a chronic recurring pain pattern?
- Does ejaculation, sitting, bowel strain or stress change the pain?
- Would pelvic floor assessment be appropriate after infection and red flags are considered?
Where lifestyle and bodywork fit
Manual therapy may be part of care when delivered by qualified pelvic health professionals, but prostate massage should not be used as a substitute for diagnosing infection or serious disease. Lifestyle factors such as sleep, alcohol, smoking, exercise, sitting time, metabolic health, hydration, medication, stress and relationship communication can matter, but they do not all matter in the same way for every person.
What not to assume
Do not assume antibiotics are always needed, and do not assume all prostatitis-like symptoms are psychological or muscular. Another common mistake is to assume that one normal result proves everything is fine, or that one uncomfortable sensation proves serious disease. Male intimate health often needs pattern recognition, not panic and not denial.
Practical next step
For acute symptoms, seek medical review. For persistent patterns, build a care plan that may include urology, pelvic floor physiotherapy and pain-informed lifestyle changes. If symptoms are mild, stable and clearly linked with lifestyle, the next step may be observation and a routine appointment. If symptoms are sudden, severe, progressive or associated with red flags, the next step is medical care. If the concern is fertility, hormones or erectile function, objective testing usually gives a better starting point than guessing.
The bottom line is simple: understand the anatomy, describe the pattern, respect red flags, and keep wellbeing practices in their proper lane. That sequence protects both health and dignity.
How to read change over time
For Prostatitis Symptoms, Causes and Treatment, trend matters because the same symptom can sit in different categories. A mild recurring pattern may call for routine review, habit tracking or pelvic floor assessment. A sudden severe version of the same region may call for urgent care. A long-term sexual or urinary change may call for risk review and testing. The reader should avoid both extremes: ignoring change because it is embarrassing, or treating every variation as a crisis.
Reader checklist
- Write the first date, main location, intensity and whether the symptom is improving, stable or worsening.
- Record urinary, sexual, bowel, pain, sleep, medication and stress changes on the same page.
- Separate urgent signs from non-urgent discomfort before considering lifestyle or bodywork options.
- Ask whether objective testing would answer the question better than self-monitoring.
- Keep consent, hygiene, scope and referral rules visible if any practitioner offers bodywork.
Bacterial prostatitis versus chronic pelvic pain
Acute bacterial prostatitis usually looks like illness, not just discomfort. Fever, chills, painful urination, pelvic pain, difficulty urinating and feeling unwell push the pattern toward urgent medical assessment. Chronic bacterial prostatitis is different: recurrent urinary tract infection patterns may point to bacteria that persist or return. Chronic prostatitis/chronic pelvic pain syndrome is different again. It can produce real pain and urinary or sexual symptoms without a clear ongoing bacterial infection.
This distinction protects the reader from two common errors. The first error is delaying antibiotics or urgent care when infection is plausible. The second error is taking repeated antibiotics or repeated prostate stimulation when the pattern is actually chronic pelvic pain, pelvic floor overactivity, nerve sensitivity or bladder behavior. Both errors can keep a man stuck.
- Acute bacterial pattern: fever, chills, acute illness, painful urination, severe symptoms.
- Chronic bacterial pattern: recurring infection evidence and urinary symptoms.
- CPPS pattern: pain for months, flares, pelvic floor overlap, often no clear bacterial cause.
Pain after ejaculation
Pain after ejaculation can involve the prostate, seminal vesicles, urethra, pelvic floor muscles, nerves or inflammation. It may appear with prostatitis, chronic pelvic pain syndrome, pelvic floor overactivity, infection, anxiety-driven guarding or irritation after repeated sexual activity. The symptom deserves careful language because it is intimate, frightening and easy to over-interpret.
A useful note for care is simple: where the pain is felt, when it begins, how long it lasts, whether urination burns, whether fever or blood is present, whether sitting worsens it and whether it repeats. Pain after ejaculation with fever, blood, discharge or severe urinary symptoms belongs in a medical pathway. Recurrent pain without infection may still deserve urology and pelvic floor assessment.
Professional medical sources
- NIDDK: Prostatitis and inflammation of the prostate
- NIDDK: Enlarged prostate, benign prostatic hyperplasia
- NCI: Prostate cancer screening PDQ
- NCI: PSA test fact sheet
- CDC: Prostate cancer screening
- CDC: Prostate cancer symptoms
- AUA: Male chronic pelvic pain guideline
- EAU: Chronic pelvic pain guidelines
- Cochrane: Interventions for chronic prostatitis and chronic pelvic pain
- NIDDK: Urinary retention
- NCI: Genetics of prostate cancer PDQ
- NCCIH: Saw palmetto and BPH evidence
- MedlinePlus: Male reproductive system
- NIDDK: Prostate problems
- WHO: Infertility fact sheet